Drugs, Health Technologies, Health Systems
Reimbursement Recommendation
Pembrolizumab (Keytruda)
Indication: For the treatment of adult patients, in combination with paclitaxel, with or without bevacizumab, with platinum-resistant epithelial ovarian, fallopian tube, or primary peritoneal carcinoma whose tumours express PD-L1 (CPS ≥ 1) as determined by a validated test, and who have received 1 or 2 prior systemic treatment regimens
Sponsor: Merck Canada Inc.
Final recommendation: Reimburse with conditions
Summary
What Is the Reimbursement Recommendation for Keytruda?
Canada’s Drug Agency (CDA-AMC) recommends that Keytruda should be reimbursed by public drug plans for the treatment of adult patients, in combination with paclitaxel, with or without bevacizumab, with platinum-resistant epithelial ovarian, fallopian tube, or primary peritoneal carcinoma whose tumours express PD-L1 (combined positive score [CPS] ≥ 1) as determined by a validated test, and who have received 1 or 2 prior systemic treatment regimens if certain conditions are met.
Why Did CDA-AMC Recommend Reimbursement?
The pan-Canadian Oncology Drug Review Expert Review Committee (pERC) determined that Keytruda plus paclitaxel, with or without bevacizumab, demonstrates acceptable clinical value versus placebo plus paclitaxel, with or without bevacizumab, in patients with platinum-resistant epithelial ovarian, fallopian tube, or primary peritoneal carcinoma whose tumours express PD-L1 and who have received 1 or 2 prior systemic treatment regimens. This determination was enough for pERC to recommend that Keytruda be reimbursed. Given that Keytruda is expected to be an additive treatment to paclitaxel with or without bevacizumab, acceptable clinical value refers to incremental value compared to paclitaxel with or without bevacizumab.
Evidence from a clinical trial showed that Keytruda plus paclitaxel, with or without bevacizumab, likely results in improvements in progression-free survival (PFS) and overall survival (OS) in patients with platinum-resistant epithelial ovarian, fallopian tube, or primary peritoneal carcinoma whose tumours express PD-L1 and who have received 1 or 2 prior systemic treatment regimens when compared to placebo plus paclitaxel, with or without bevacizumab. Clinical trial data suggested that Keytruda may result in little to no difference in health-related quality of life (HRQoL) compared to placebo. The safety profile of Keytruda was considered to be consistent with the known safety profile of immunotherapy and expected to be manageable.
Keytruda, when added on to paclitaxel with or without bevacizumab, addresses some of the needs identified by patients by delaying disease progression and prolonging survival.
Which Patients Are Eligible for Coverage?
Keytruda should only be covered to treat adult patients with platinum-resistant epithelial ovarian, fallopian tube, or primary peritoneal carcinoma who have received 1 or 2 prior lines of treatment, have tumours with a PD-L1 CPS of 1 or higher, and a good performance status. Keytruda should not be used in patients with primary platinum-refractory disease or patients with mucinous tumours.
What Are the Conditions for Reimbursement?
Keytruda should only be reimbursed if it is initiated by clinicians with expertise in the management of epithelial ovarian cancer and immune checkpoint inhibitor therapy and if the cost of Keytruda is reduced.
Review Background
Disease background: Ovarian cancer is the 10th most frequent cancer and the fifth-leading cause of cancer deaths in females in Canada. In 2025 alone, an estimated 3,100 females in Canada were diagnosed with ovarian cancer; between 2015 and 2017, the predicted overall 5-year survival rate for patients with ovarian cancer was 44%. Epithelial ovarian carcinomas (EOCs), which include fallopian tube and primary peritoneal carcinoma, are the most common type of ovarian cancer that develops in the tissue surrounding the ovaries.
Indication and reimbursement request: Pembrolizumab (Keytruda) has been approved by Health Canada for the treatment of adult patients, in combination with paclitaxel, with or without bevacizumab, with platinum-resistant epithelial ovarian, fallopian tube, or primary peritoneal carcinoma whose tumours express PD-L1 (CPS ≥ 1) as determined by a validated test, and who have received 1 or 2 prior systemic treatment regimens. The sponsor is seeking reimbursement for this patient population.
Drug under review: Pembrolizumab is a high-affinity antibody against PD-1. It is administered by IV infusion, and the dosage recommended in the product monograph is 200 mg every 3 weeks or 400 mg every 6 weeks.
Treatment costs: At the submitted price of $4,400.00 per 4 mL, the 28-day cost of pembrolizumab is expected to be $11,733 per patient based on the Health Canada–recommended dosage. Pembrolizumab is indicated for use in combination with paclitaxel with or without bevacizumab; the cost of the regimen is expected to cost $20,870 per patient per 28-day period with bevacizumab and cost $18,921 without bevacizumab over the same period.
Highlights of Input From Interested Parties
The patient groups (Ovarian Cancer Canada and the Canadian Cancer Survivor Network [CCSN], with the support of the Colorectal Cancer Resource & Action Network [CCRAN]) noted the following regarding impacts of the disease, unmet needs, and important outcomes:
Patients emphasized how ovarian cancer has devastating impacts on various areas of their lives including physical activity, self-esteem, sleep and fatigue, and the ability to care for their family and themselves. It was also noted that the impacts extend beyond the patient, with caregivers also reporting a reduced quality of life.
There remains an unmet need for an effective treatment that limits progression, improves survival, and reduces side effects, which include fatigue, bowel movement changes, and neuropathy.
The most important treatment goals for patients are prolonging life and providing a cure, maintaining quality of life, delaying the onset of new symptoms, reducing side effects, and ensuring ease of use.
The clinician groups (Ontario Health [Cancer Care Ontario] [OH (CCO)] Gynecologic Cancer Drug Advisory Committee [Gyne DAC] and the Gynecologic Tumour Group [British Columbia]) and the clinical experts consulted by CDA-AMC noted the following regarding unmet needs arising from the disease and place in therapy for the drug under review:
The clinical experts consulted for this review and OH (CCO) Gyne DAC agreed there remains a need for a treatment with improved survival and reduced side effects thereby increasing quality of life. The consulted clinical experts further felt there was an unmet need for improved response rates.
Pembrolizumab may cause a shift in the treatment paradigm because it would be the preferred treatment option for patients with PD-L1–positive EOC that has become platinum resistant following 1 or 2 lines of treatment.
The participating public drug programs provided input regarding considerations for initiation, renewal, discontinuation, and prescribing of therapy; health system implementation considerations; relevant comparators; system and economic considerations; and the potential need for a provisional funding algorithm. Health system implementation considerations include feasibility of adoption and other health system implementation considerations. System and economic considerations include drug administration considerations and other system and economic considerations.
Recommendation
With a vote of 14 in favour to 0 against, pERC recommends that pembrolizumab, in combination with paclitaxel, with or without bevacizumab, be reimbursed for the treatment of adult patients with platinum-resistant epithelial ovarian, fallopian tube, or primary peritoneal carcinoma whose tumours express PD-L1 (CPS ≥ 1) as determined by a validated test and who have received 1 or 2 prior systemic treatment regimens.
Table 1: Reimbursement Conditions and Reasons
Reimbursement condition | Reason | Implementation guidance |
|---|---|---|
Initiation | ||
1. Treatment with pembrolizumab plus paclitaxel, with or without bevacizumab, should be initiated in adult patients who have all the following criteria: 1.1. epithelial ovarian, fallopian tube, or primary peritoneal carcinoma 1.2. prior treatment with 1 or 2 lines of systemic treatment regimens, including at least 1 prior platinum-based therapy 1.3. platinum-resistant disease defined as radiographic evidence of disease progression within 6 months after the last dose of platinum-based chemotherapy for EOC 1.4. tumour with PD-L1 CPS ≥ 1 as confirmed by a validated test 1.5. good performance status. | Evidence from the KEYNOTE-B96 trial demonstrated that treatment with pembrolizumab, in combination with weekly paclitaxel and with or without bevacizumab, resulted in added clinical benefit in patients who fulfilled these characteristics. | Condition 1.2: pERC agreed with the clinical experts that patients with more than 2 lines of prior systemic therapy before progressing to platinum-resistant disease are likely to benefit from addition of pembrolizumab to paclitaxel with or without bevacizumab and should be considered on a case-by-case basis. In the KEYNOTE-B96 trial, eligible patients must have received at least 4 cycles of platinum-based therapy in the first line of therapy. pERC agreed with the clinical experts that patients who received fewer than 4 cycles of a prior platinum-based regimen due to intolerance, may be considered eligible to receive pembrolizumab plus paclitaxel, with or without bevacizumab. Condition 1.5: The KEYNOTE-B96 trial included patients with an ECOG Performance Status of 0 or 1. pERC agreed with the clinical experts that selected patients with an ECOG Performance Status of 2 could be considered for treatment at the discretion of the treating physician. |
2. Pembrolizumab should not be reimbursed in patients who have: 2.1. primary platinum-refractory disease, defined as disease that progresses during or within 28 days of first exposure to platinum-based treatment 2.2. mucinous tumours. | Patients with platinum-refractory disease were excluded from the KEYNOTE-B96 trial. pERC did not review any evidence to suggest an additional benefit of pembrolizumab plus paclitaxel, with or without bevacizumab, in patients with platinum-refractory disease and in those with mucinous tumours. | — |
Discontinuation | ||
3. Reimbursement of pembrolizumab in combination with paclitaxel, with or without bevacizumab, should be discontinued upon occurrence of any of the following: 3.1. disease progression 3.2. unacceptable toxicity 3.3. completion of 24 months of treatment with pembrolizumab. | This condition reflects the treatment discontinuation criteria used in the KEYNOTE-B96 trial. | Condition 3.2: pERC agreed with the clinical experts that if treatment with the pembrolizumab combination was temporarily interrupted due to intolerance or toxicity, treatment may be resumed at any time provided there was no evidence of disease progression during the initial treatment period. Condition 3.3: pERC agreed with the clinical experts that if treatment with the pembrolizumab combination was discontinued before the completion of 2 years of therapy for reasons other than disease progression, or after completion of the 2 years of therapy, it would be reasonable to consider re-treatment with pembrolizumab (up to 12 months) plus paclitaxel, with or without bevacizumab, upon disease progression |
4. If 1 component of the combination therapy with pembrolizumab plus paclitaxel, with or without bevacizumab, is discontinued permanently because of tolerability concerns, the patient can continue with other components at the discretion of the treating physician until the criteria in Condition 3 are met. | In the KEYNOTE-B96 trial, each component of the treatment (pembrolizumab, paclitaxel, or bevacizumab) could be interrupted or discontinued due to toxicity, and the other components could be continued until the treatment discontinuation criteria were met. | — |
Prescribing | ||
5. Treatment with pembrolizumab plus paclitaxel, with or without bevacizumab, should be initiated by clinicians with expertise in management of epithelial ovarian cancer and immune checkpoint inhibitor therapy. | This is meant to ensure that pembrolizumab is prescribed for appropriate patients and that adverse effects are managed in an optimized and timely manner. | — |
6. Pembrolizumab should be prescribed in combination with paclitaxel, with or without bevacizumab, for eligible patients. | In the KEYNOTE-B96 trial, pembrolizumab was used in combination with paclitaxel, with or without bevacizumab. pERC did not review any evidence to suggest an additional benefit of pembrolizumab as monotherapy or in combination with other treatments in the patient population of interest. | pERC agreed with the clinical experts that, at the time of implementation of the reimbursement recommendation, there may be a need for a limited time frame for adding pembrolizumab to the treatment of patients who have recently started treatment with paclitaxel with or without bevacizumab and have no evidence of disease progression. pERC agreed with the clinical experts that a weekly paclitaxel schedule may be preferred over an every-3-weeks regimen given the potential synergy of this dosing schedule with immune checkpoint inhibitor therapy. The effects of 3-weekly dosing with paclitaxel were not assessed in the KEYNOTE-B96 trial. pERC agreed with the clinical experts that patients who experience a severe hypersensitivity reaction to, or an adverse event from, paclitaxel can switch to weekly nab-paclitaxel. pERC did not review any evidence to suggest an additional benefit of pembrolizumab in combination with other treatments in the patient population of interest. |
Pricing | ||
7. A reduction in price. | Using the CDA-AMC base-case analysis, the ICER for pembrolizumab plus paclitaxel, with or without bevacizumab, was $149,712 per QALY gained when compared with paclitaxel with or without bevacizumab in the indicated population. A band 3a price reduction would be required to achieve cost-effectiveness at a $50,000 per QALY gained threshold. A band 2a price reduction would be required to achieve cost-effectiveness at a $100,000 per QALY gained threshold. Exact price reductions at any given willingness-to-pay threshold can be found in the CDA-AMC main report and Supplemental Material document. | The CDA-AMC analysis is based on public list prices for all treatments. Further price reductions may be required if there are price arrangements (discounts) currently in place for any treatment included in the economic analysis. |
Feasibility of adoption | ||
8. The organizational feasibility of conducting PD-L1 testing for EOC must be addressed. | PD-L1 testing is used to inform treatment eligibility with pembrolizumab in patients with platinum-resistant EOC. pERC noted that PD-L1 testing is not currently part of routine care or funded for patients of interest in this review. | PD-L1 testing is routinely conducted for some other cancer types. Minimal additional health system impacts are anticipated if testing were to be expanded to patients with platinum-resistant EOC. |
CDA-AMC = Canada’s Drug Agency; CPS = combined positive score; ECOG = Eastern Cooperative Oncology Group; EOC = epithelial ovarian carcinomas; ICER = incremental cost-effectiveness ratio; pERC = pan-Canadian Oncology Drug Review Expert Review Committee; QALY = quality-adjusted life-year.
aFor the statement regarding the size of the price reduction required, band 1 = 1% to 24%, band 2 = 25% to 49%, band 3 = 50% to 74%, and band 4 = 75% or greater.
Rationale for the Recommendation
Clinical Value
Based on the totality of the clinical evidence, pERC concluded that pembrolizumab in combination with paclitaxel, with or without bevacizumab, demonstrates acceptable clinical value compared with paclitaxel, with or without bevacizumab, in patients with platinum-resistant EOC whose tumours express PD-L1 and who have received 1 or 2 prior systemic treatment regimens. Because pembrolizumab is expected to be an additive treatment to paclitaxel with or without bevacizumab, acceptable clinical value refers to incremental value compared to paclitaxel, with or without bevacizumab.
Evidence from 1 double-blind, phase III, randomized controlled trial (KEYNOTE-B96; N = 643) was reviewed by pERC. Results from the subgroup analysis of patients with a PD-L1 CPS of 1 or higher (n = 466) demonstrated that pembrolizumab plus paclitaxel, with or without bevacizumab, likely results in added clinical value in PFS and OS in patients with platinum-resistant EOC whose tumours express PD-L1 and who have received 1 or 2 prior systemic treatment regimens, when compared to placebo plus paclitaxel, with or without bevacizumab. After a median follow-up time of 18.2 months for the pembrolizumab group and 14.0 months for the placebo group, the median PFS assessed by the investigator (primary end point) was 8.3 months (95% confidence interval [CI], 7.0 to 9.5 months) in the pembrolizumab group compared to 7.2 months (95% CI, 6.2 to 8.1 months) in the placebo group (hazard ratio [HR] = 0.76; 95% CI, 0.62 to 0.93). In patients whose tumours expressed PD-L1, the median OS was 18.2 months (95% CI, 15.3 to 21.3 months) in the pembrolizumab group compared to 14.0 months (95% CI, 12.5 to 16.1 months) in the placebo group (HR = 0.76; 95% CI, 0.62 to 0.93). In the total trial population, the median OS was 17.7 months (95% CI, 15.2 to 19.2 months) in the pembrolizumab group compared to 14.0 months (95% CI, 12.5 to 15.6 months) in the placebo group (HR = 0.82; 95% CI, 0.69 to 0.97).
Patient groups, clinician groups, and clinical experts consulted by CDA-AMC identified the need for treatments that are more effective in prolonging survival and delaying disease progression while maintaining quality of life and minimizing side effects. pERC concluded that pembrolizumab, when added on to paclitaxel, with or without bevacizumab, addresses the need for a more effective treatment that may delay disease progression and prolong survival. Results from the KEYNOTE-B96 trial suggested that pembrolizumab may result in little to no difference in HRQoL compared to placebo. However, pERC was unable to draw conclusions on HRQoL due to substantial proportions of missing data and imprecise estimates. In the trial, a higher proportion of patients in the pembrolizumab group experienced a serious adverse event, or an adverse event resulting in treatment discontinuation, than in the placebo group. pERC agreed with the clinical experts that, overall, the harms associated with pembrolizumab appeared consistent with its known safety profile and are considered manageable.
Developing the Recommendation
The determination of acceptable clinical value was sufficient for pERC to recommend reimbursement of pembrolizumab in combination with paclitaxel, with or without bevacizumab. As part of the deliberation on whether to recommend reimbursement, the committee also considered unmet clinical need, unmet nonclinical need, and health inequity. Information on this discussion is provided in the Unmet Clinical Need and Distinct Social and Ethical Considerations domains in the Summary of Deliberation section.
Because pERC recommended that pembrolizumab in combination with paclitaxel, with or without bevacizumab, be reimbursed, the committee also deliberated on whether reimbursement conditions should be added to address important economic considerations, health system impacts, or social and ethical considerations, or to ensure clinical value is realized. The resulting reimbursement conditions, with accompanying reasons and implementation guidance, are stated in Table 1.
Summary of Deliberation
pERC considered all domains of value of the deliberative framework before developing its recommendation: clinical value, unmet clinical need, distinct social and ethical considerations, economic considerations, and impacts on health systems. For further information on the domains of value, refer to Expert Committee Deliberation at Canada’s Drug Agency.
The committee considered the following key discussion points, organized by the 5 domains of value.
Clinical Value
Appropriate comparators: The clinical experts consulted for this review indicated that current treatment options for patients with platinum-resistant EOC include single-agent nonplatinum chemotherapy (e.g., paclitaxel, topotecan, gemcitabine, or liposomal doxorubicin) with or without bevacizumab. pERC agreed that the comparator used in the KEYNOTE-B96 trial (i.e., placebo plus paclitaxel with or without bevacizumab) was an appropriate comparator in the target population. The committee discussed that mirvetuximab soravtansine has previously received recommendation for reimbursement from pERC and it was therefore considered a relevant comparator for the subset of patients who have folate receptor alpha-positive disease. However, it was noted that pan-Canadian Pharmaceutical Alliance (pCPA) negotiations for mirvetuximab soravtansine concluded in May 2026 without an agreement, and it is currently not publicly funded in Canada.
Efficacy versus placebo and paclitaxel with or without bevacizumab: pERC discussed evidence from the KEYNOTE-B96 trial, highlighting that the current review focused on the subgroup of patients from the trial whose tumours express PD-L1. In the trial, 72.5% of patients had PD-L1 CPS of 1 or higher. Findings in the subgroup of patients with PD-L1–positive tumours demonstrated that, compared to placebo plus paclitaxel with or without bevacizumab (n = 232), treatment with pembrolizumab plus paclitaxel with or without bevacizumab (n = 234) results in an increase in the proportion of patients remaining progression-free at 6 months (between-group difference = █████ ███ ███) and 12 months (between-group difference = █████ ███ ███). Although 6-month OS rates were similar in both treatment groups (between-group difference = █████ ███ ███), pembrolizumab resulted in an increase in the proportion of patients surviving at 18 months (between-group difference = █████ ███ ███). HRQoL outcomes results, which were limited by low completion rates, suggested that pembrolizumab may result in little to no difference in HRQoL compared to placebo, and its impact on abdominal or gastrointestinal symptoms remains uncertain.
Clinical importance of treatment effects: pERC noted important outcomes for patients include prolonging life, remaining progression-free, maintaining quality of life, and reducing harms which were assessed in the KEYNOTE-B96 trial. pERC discussed that the difference between treatment groups in the percentage of patients remaining progression-free until 6 and 12 months were likely clinically relevant based on expert input that a 5% difference in PFS would be a clinically important effect. Although OS results at 6 months did not reach the clinically important difference threshold of 5% suggested by experts, pERC noted that the difference between treatment groups in the percentage of patients surviving until 18 months was likely clinically relevant using a 10% threshold suggested by the experts. Based on established minimally important difference thresholds identified in the literature (i.e., 9 points for improvement and −7 points for deterioration), pERC concluded that the trial results suggest pembrolizumab may result in little to no difference in HRQoL compared to placebo.
Certainty of the evidence: Using the Grading of Recommendations Assessment, Development and Evaluation (GRADE) approach, the certainty of evidence in the percentage of patients surviving to 6 and 18 months and remaining progression-free until 6 and 12 months was rated as moderate due to serious imprecision in the between-group differences. HRQoL was rated as low due to serious risk of bias stemming from missing data and imprecision. The abdominal and gastrointestinal symptoms score was rated as very low due to serious risk of bias stemming from missing data, modification of the instrument, and imprecision. Grade 3 to 4 immune-mediated adverse events were rated as moderate due to imprecision in the between-group differences.
Efficacy versus mirvetuximab soravtansine: pERC noted that an indirect treatment comparison to inform on the effects of pembrolizumab and paclitaxel, with or without bevacizumab, versus mirvetuximab soravtansine was deemed infeasible due to major differences across trial populations and study designs.
Patient eligibility: Both the reimbursement request under review and the Health Canada indication were restricted to patients with platinum-resistant EOC whose tumours express PD-L1 and who have received 1 or 2 prior systemic treatment regimens. pERC heard from clinical expects that an estimated 25% of patients receive 3 or more lines of platinum-based therapy before their tumours become platinum resistant. pERC noted that no data were included in this review to show the effects of pembrolizumab with paclitaxel, with or without bevacizumab, in patients with these tumours. However, the committee agreed with the clinician groups and clinical experts consulted for this review that patients who have received more than 2 lines of prior systemic therapy before progression to platinum-resistant disease are likely to benefit from the addition of pembrolizumab to paclitaxel, with or without bevacizumab, and may be considered eligible to receive the combination therapy with pembrolizumab. pERC additionally discussed that, in the final analysis for the KEYNOTE-B96 trial, efficacy results were generally consistent in the overall population (i.e., not restricted by PD-L1 status) with those in the subgroup of patients with PD-L1 expression. pERC agreed with the clinical experts that jurisdictions may wish to consider case-by-case eligibility for pembrolizumab for patients with a PD-L1 CPS less than 1, at the discretion of the treating physician.
Clinical value: Based on the preceding considerations, pERC determined there was added clinical value versus paclitaxel, with or without bevacizumab.
Unmet Clinical Need
Input on unmet clinical need: Based on patient and clinician input, pERC acknowledged a need for additional effective treatments for patients with platinum-resistant EOC who have received 1 or 2 prior systemic therapies that can prolong survival, delay disease progression, maintain quality of life, and reduce side effects.
Severity of the disease: Ovarian cancer is the 10th most frequent cancer and the fifth-leading cause of cancer deaths in females in Canada, and approximately 90% of ovarian cancers are classified as EOC. Based on patient and clinician input, pERC noted that platinum-resistant EOC is a life-threatening and debilitating disease. Patients noted that EOC negatively impacts various aspects of their lives, including physical activity, self-esteem, sleep and fatigue, and the ability to care for their family and themselves. Commonly reported symptoms include changes in bowel habits, pain and discomfort, unintended weight loss or gain, and a general sense of reduced quality of life.
Availability of treatment options: pERC discussed that currently available treatment options for patients with platinum-resistant EOC whose tumours express PD-L1 are limited to nonplatinum chemotherapy, with or without bevacizumab. Although mirvetuximab soravtansine can be used in the subset of patients with folate receptor alpha-positive disease, negotiations for public funding concluded in May 2026 without an agreement and, therefore, it is currently not publicly funded in Canada. Patient input emphasized the importance of having multiple treatment options to allow patients and their health care team to select an approach that aligns with individual physical, emotional, social, financial, and logistical needs.
Distinct Social and Ethical Considerations
Input on unmet nonclinical need: Patients reported travel as a moderate barrier to accessing treatment due to requiring caregiver support and geographic distance from the treatment centres. pERC discussed patient input, highlighting that pembrolizumab may offer easier symptom management with fewer side effects, which could help address access-related challenges, such as visit frequency; time away from work, school, or family; and transportation burden. These benefits may extend beyond the patient by reducing caregiver burden.
Equity considerations: pERC discussed that, according to the consulted clinical experts, pembrolizumab is currently available and accessible on the market and patients can receive treatment at private infusion clinics if they can afford to pay for it, thereby creating a disadvantage.
Economic Considerations
Health impacts of pembrolizumab plus paclitaxel with or without bevacizumab versus relevant comparators: Pembrolizumab plus paclitaxel with or without bevacizumab is predicted to be associated with a gain of gain of 0.80 life-years compared to paclitaxel with or without bevacizumab and may result in a gain of 0.63 quality-adjusted life-years (QALYs) compared to paclitaxel with or without bevacizumab over a lifetime (39-year) horizon.
Cost of pembrolizumab plus paclitaxel with or without bevacizumab versus relevant comparators: Pembrolizumab and paclitaxel with or without bevacizumab is predicted to be associated with higher costs to the health care system than paclitaxel with or without bevacizumab (incremental costs = $96,018) over a lifetime (39-year) horizon, primarily driven by increased costs associated with drug acquisition.
Key findings of the economic evaluation: Based on the submitted evidence using the sponsor’s cost-utility analysis, the CDA‑AMC base-case analysis estimated that the incremental cost-effectiveness ratio (ICER) for pembrolizumab plus paclitaxel with or without bevacizumab in the indicated population was $149,712 per QALY gained when compared with paclitaxel with or without bevacizumab (Figure 1).
Figure 1: Estimate of the ICER Used by pERC to Inform the Price Condition
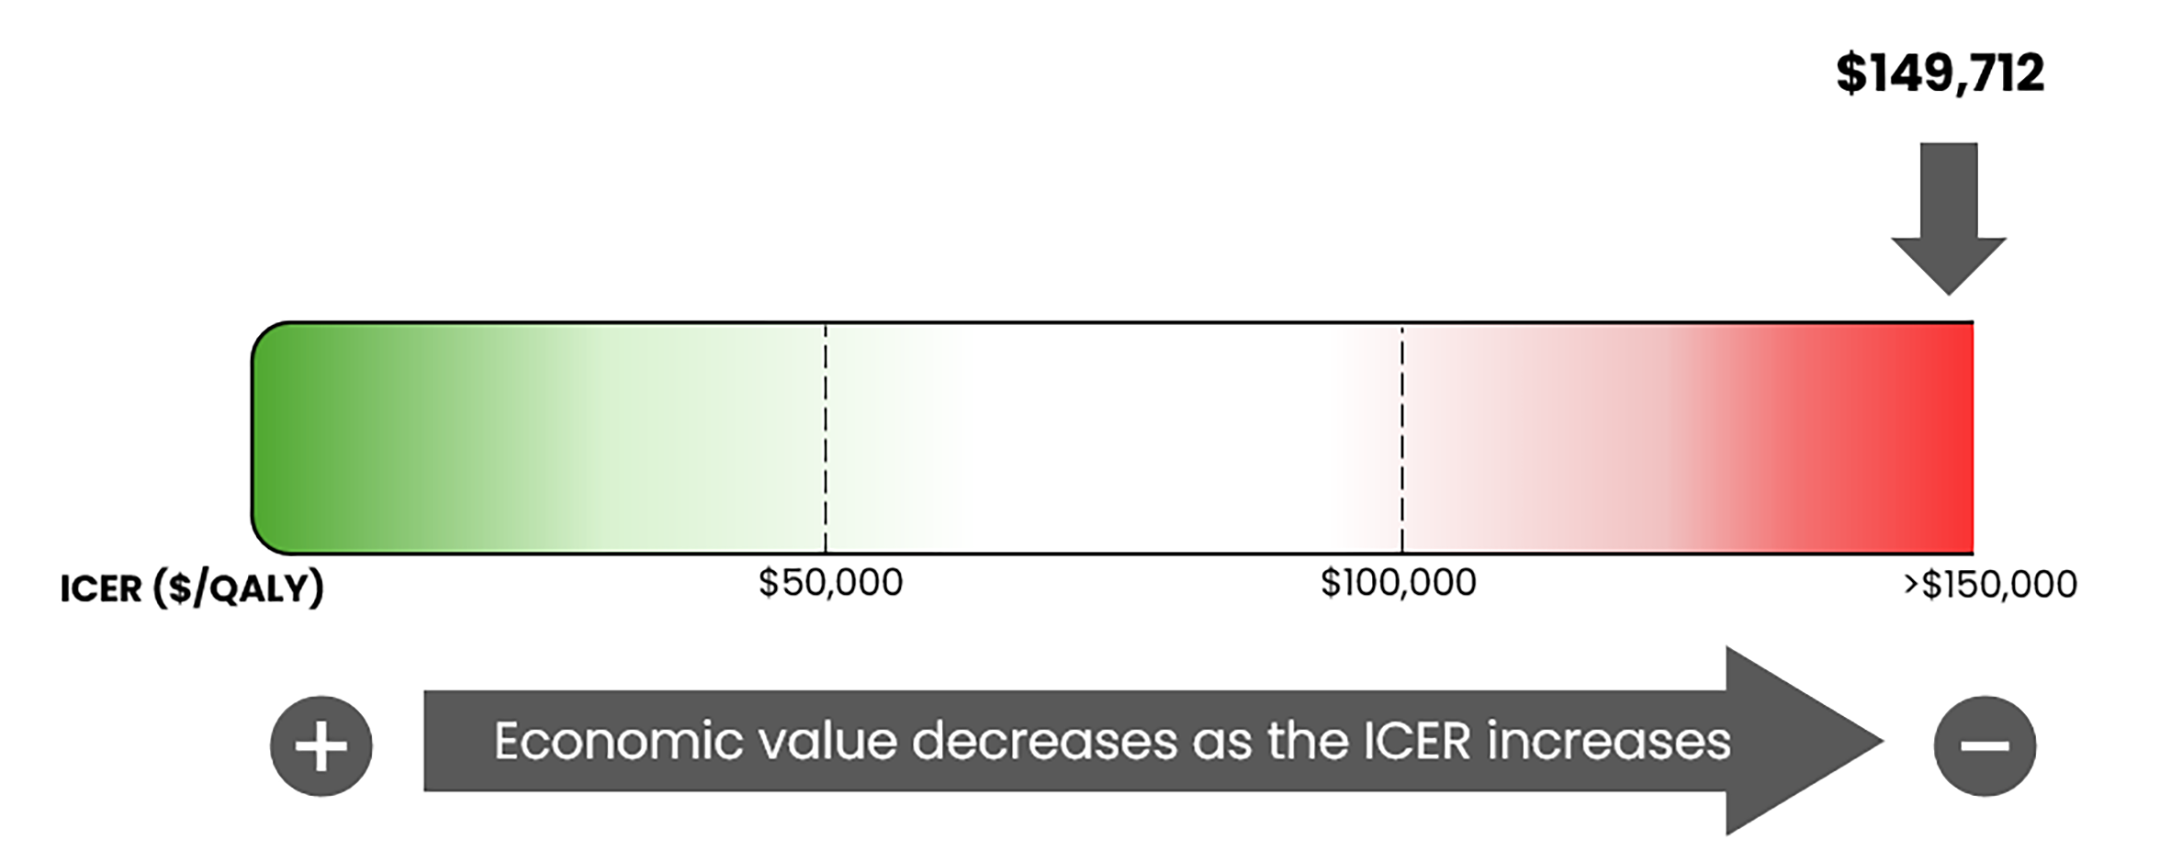
ICER = incremental cost-effectiveness ratio; pERC = pan-Canadian Oncology Drug Review Expert Review Committee; QALY = quality-adjusted life-year.
Certainty of the evidence: Due to uncertainty around flat versus weight-based dosing and the lack of long-term evidence, extrapolations of OS and PFS, higher price reductions than those presented may therefore be required to achieve cost-effectiveness at a given willingness-to-pay threshold.
Impacts on Health Systems
Anticipated budget impact: The estimated budget impact of reimbursing pembrolizumab and paclitaxel with or without bevacizumab for the indicated population will be approximately $42 million over the first 3 years of reimbursement compared to the amount currently spent on comparators. The expenditure on pembrolizumab over this period is predicted to be $39 million (pembrolizumab and paclitaxel with bevacizumab = $70 million). The actual budget impact of reimbursing pembrolizumab will depend on eligible patient population size and the pembrolizumab dosing regimen.
Testing procedure considerations: In Canada, PD-L1 testing is not a current part of care or funded for patients with ovarian cancer. pERC noted that minimal impacts to establishing PD-L1 testing is anticipated since it is currently available and is performed as the standard of care for some other cancer types.
Sources of Information Used by the Committee
To make its recommendation, the committee considered the following information (links to the full documents for the review can be found on the project web page):
the CDA-AMC review of the clinical and pharmacoeconomic evidence submitted by the sponsor, as well as relevant ethical issues related to pembrolizumab (refer to the Main Report and Supplemental Material document)
the sponsor’s comments on the draft report and the CDA-AMC responses
patients’ perspectives gathered by 2 patient groups, Ovarian Cancer Canada and CCSN, with the support of the CCRAN
input from 2 clinician groups, OH (CCO) Gyne DAC and the Gynecologic Tumour Group (British Columbia)
input from public drug programs that participate in the reimbursement review process (refer to the Supplemental Material document)
input from 2 clinical experts with expertise in the management of ovarian cancer consulted by CDA-AMC.
pERC Information
Members of the Committee
Dr. Catherine Moltzan (Chair), Dr. Kelvin Chan (Vice-Chair), Paul Agbulu, Dr. Phillip Blanchette, Dr. Matthew Cheung, Annette Cyr, Dr. Jennifer Fishman, Dr. Prafull Ghatage, Dr. Jason Hart, Terry Hawrysh, Dr. Yoo‑Joung Ko, Dr. Aly‑Khan Lalani, Amy Peasgood, Dr. Anca Prica, Dr. Michael Raphael, Dr. Adam Raymakers, Dr. Patricia Tang, Dr. Pierre Villeneuve, and Danica Wasney.
Meeting date: August 11, 2026
Regrets: Four expert committee members did not attend.
Conflicts of interest: One expert committee member did not participate due to considerations of conflict of interest.
ISSN: 2563-6596
Canada’s Drug Agency (CDA-AMC) is a pan-Canadian health organization. Created and funded by Canada’s federal, provincial, and territorial governments, we’re responsible for driving better coordination, alignment, and public value within Canada’s drug and health technology landscape. We provide Canada’s health system leaders with independent evidence and advice so they can make informed drug, health technology, and health system decisions, and we collaborate with national and international partners to enhance our collective impact.
Disclaimer: CDA-AMC has taken care to ensure that the information in this document was accurate, complete, and up to date when it was published, but does not make any guarantee to that effect. Your use of this information is subject to this disclaimer and the Terms of Use at cda-amc.ca.
The information in this document is made available for informational and educational purposes only and should not be used as a substitute for professional medical advice, the application of clinical judgment in respect of the care of a particular patient, or other professional judgments in any decision-making process. You assume full responsibility for the use of the information and rely on it at your own risk.
CDA-AMC does not endorse any information, drugs, therapies, treatments, products, processes, or services. The views and opinions of third parties published in this document do not necessarily reflect those of CDA-AMC. The copyright and other intellectual property rights in this document are owned by the Canadian Agency for Drugs and Technologies in Health (operating as CDA-AMC) and its licensors.
Questions or requests for information about this report can be directed to Requests@CDA-AMC.ca